Genetic Mutations and Congenital Musculoskeletal Disorders—Comprehensive Treatment
The Paley European Institute in Warsaw specializes in the diagnosis and treatment of rare, genetically caused musculoskeletal disorders in children and adults. We treat, among other conditions, arthrogryposis, Larsen syndrome, popliteal web syndrome, and the consequences of RYR1 gene mutations. We follow methods developed at the Paley Institute (USA), one of the world’s leading centers for reconstructive orthopedics.
What are genetic mutations in orthopedics?
Genetic mutations are permanent changes in genetic material. They can disrupt the development of muscles, nerves, connective tissue, or bones even during fetal development. They can result in congenital joint contractures, dislocations, limb stiffness, webbing (skin folds crossing a joint), and deformities of the feet and spine.
A mutation can be inherited from one or both parents, or it can arise de novo—that is, for the first time in the child. Identifying the genetic cause helps establish an accurate diagnosis, predict the course of the disease, and plan safe treatment, including anesthesia.
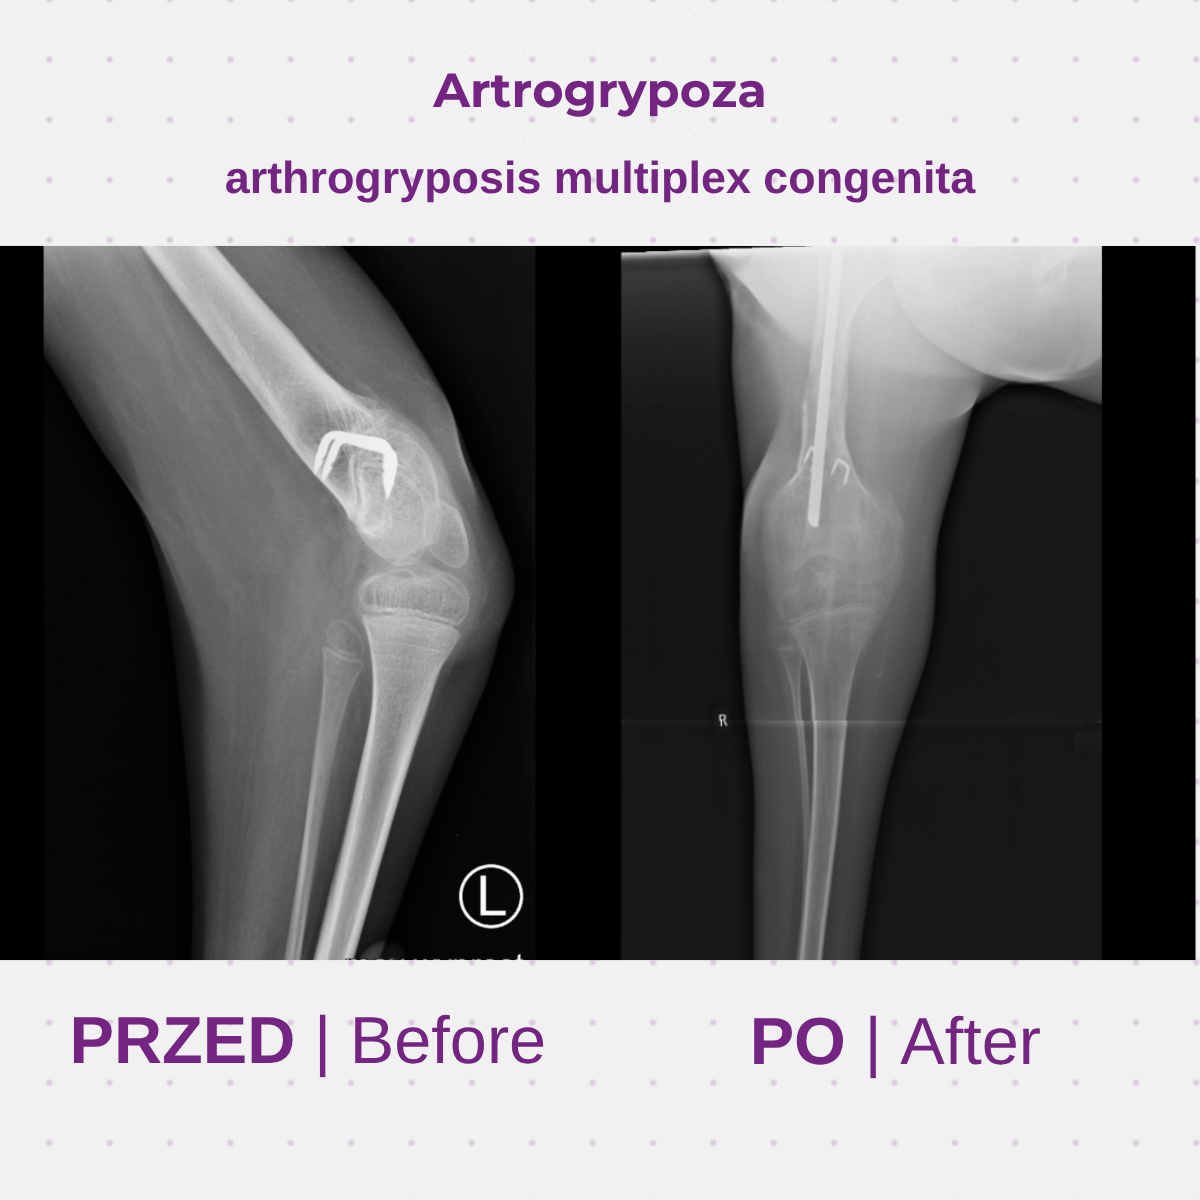
Genetic mutations
Reasons
Congenital musculoskeletal disorders may result from mutations in genes responsible for the structure of muscle proteins (e.g., RYR1, TPM2, MYH3), connective tissue and the skeleton (e.g., FLNB), or neuromuscular junctions (e.g., ECEL1). Some cases have causes other than genetic factors. These include limited fetal mobility, intrauterine factors, infections, or substances taken during pregnancy.
Symptoms
The most common symptoms include stiffness and contractures in many joints, dislocations of the hip, knee, and elbow joints, clubfoot, joint deformities, muscle weakness, and spinal curvature. The severity of symptoms can vary greatly, even within the same family.
Diagnostics
Diagnosis is based on clinical examination, imaging studies (X-ray, ultrasound, MRI), and genetic testing conducted in collaboration with a clinical geneticist. Many defects can be suspected as early as during prenatal ultrasound. A definitive diagnosis is usually established after birth.
The global standard in the treatment of rare congenital disorders
The Paley European Institute is the European branch of the Paley Orthopedic & Spine Institute in West Palm Beach, Florida. The facility is located in Warsaw, on the grounds of Medicover Hospital. Our doctors use treatment methods developed and refined by Dr. Dror Paley and his team. We treat conditions that are addressed by only a few centers worldwide.
What Sets Us Apart:
experience in treating rare genetic syndromes, which are addressed by only a few centers in Europe,
a personalized treatment plan for each patient,
a multidisciplinary team: pediatric orthopedists, surgeons, anesthesiologists, physical therapists, orthotists, and a psychologist,
anesthesia procedures tailored to patients with mutations that increase the risk of malignant hyperthermia.

When should you see a specialist?
The earlier treatment begins, the greater the chance of normal joint development and of reducing the number of surgeries in the future.
During Pregnancy – If an ultrasound reveals abnormal limb positioning, contractures, or limited fetal mobility, a prenatal consultation allows you to develop a care plan starting from the first days of life.
After birth – Stiff or dislocated joints, clubfoot, webbed fingers or toes, or abnormal positioning of the hands and wrists are indications for urgent consultation. In Larsen syndrome, reduction of dislocated joints may be necessary as early as 3–6 months of age.
During the first year of life – Physical therapy started before the child turns 1 reduces the risk of the deformity worsening.
For older children and adults – It is advisable to see a specialist if you experience a recurrence of contractures, a crouching gait, pain, rapid fatigue, spinal curvature, or difficulty with daily activities. We also invite patients who have previously been treated at other centers to schedule a consultation.

How do we treat genetic birth defects?
Treatment is a long-term process and is always tailored to the individual. We pursue it when it provides a tangible benefit to the patient’s functional status and quality of life.
Diagnostics and Planning
a detailed orthopedic examination and functional assessment,
imaging diagnostics and genetic counseling,
setting treatment goals together with the family,
a multi-stage treatment plan.
Conservative treatment
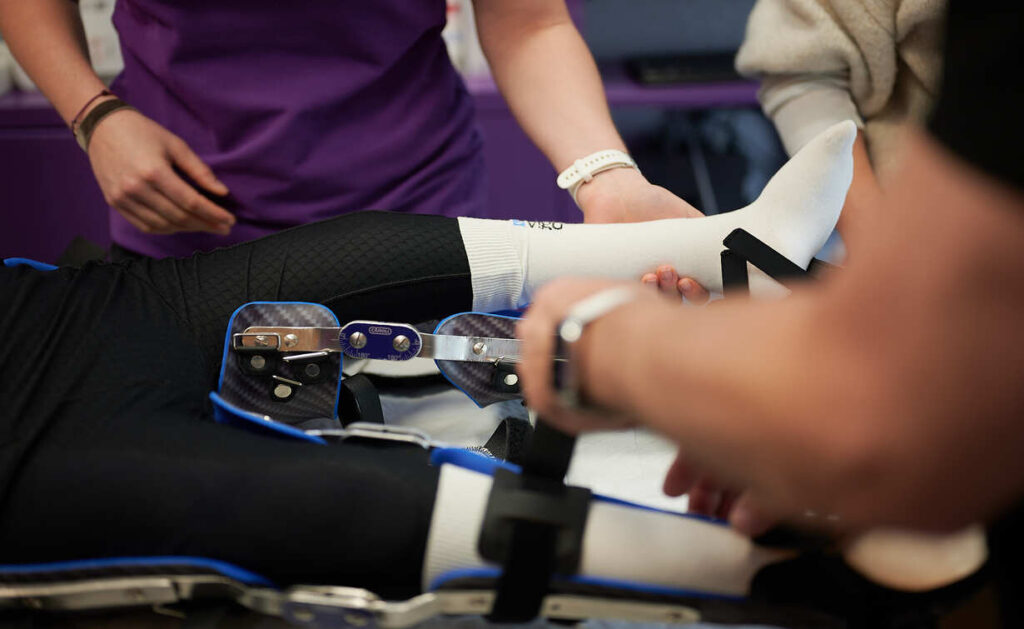
serial casting and splinting, which are the methods of first choice for clubfoot,
wrists and hands,
daytime and nighttime braces,
physical therapy starting in the first months of life (including NDT-Bobath and Vojta),
selection of orthopedic supplies.
Surgical treatment
soft tissue release and tendon lengthening,
tendon transfers,
corrective osteotomies and bone shortening,
hip, knee, foot, and upper limb reconstructions,
external fixators (Ilizarov, Taylor Spatial Frame)
growth modulation (“8-plate” plates).
Rehabilitation and Long-Term Care
intensive rehabilitation before and after surgery,
monitoring for recurrent contractures during the growth period,
collaboration with a neurologist and an orthotist,
psychological support for the child and the family.
What genetic disorders of the musculoskeletal system do we treat?
Arthrogryposis (AMC) is a condition characterized by congenital contractures of multiple joints.
Larsen syndrome is characterized by congenital dislocations of multiple joints associated with a mutation in the FLNB gene.
Popliteal web syndrome (PPS) is characterized by skin folds behind the knees, severe flexion contractures of the knees, and facial abnormalities.
Escobar syndrome is characterized by multiple joint hypermobility (multiple hypermobility syndrome).
RYR1-related myopathies are characterized by muscle weakness, contractures, scoliosis, and an increased risk of malignant hyperthermia.
Distal arthrogryposis (including mutations in TPM2, MYH3, and ECEL1) primarily affects the hands and feet. Freeman-Sheldon syndrome is one such condition.
Arthrogryposis (congenital multi-joint stiffness, AMC)
Arthrogryposis (arthrogryposis multiplex congenita, AMC) is a condition characterized by congenital contractures of at least two joints in different parts of the body. It is not a single disease. Rather, it is a symptom that can accompany several hundred different conditions. Its prevalence is estimated, depending on the source, to be between 1 in 3,000 and 1 in 10,000 births. Arthrogryposis usually does not affect intellectual development or life expectancy.
The most common form is amyoplasia. It is usually not hereditary and involves contractures of all four limbs. Distal arthrogryposis primarily affects the hands and feet and is often genetic in origin (involving, among others, the TPM2, MYH3, and ECEL1 genes). The neurogenic form results from disorders of the nervous system.
How do we treat arthrogryposis?
We begin with casting, splinting, and physical therapy starting in the first weeks of life. If necessary, we perform joint release procedures, corrective osteotomies of the femur and tibia, tendon transfers, and reconstructive surgery of the hip, knee, foot, and upper limb.
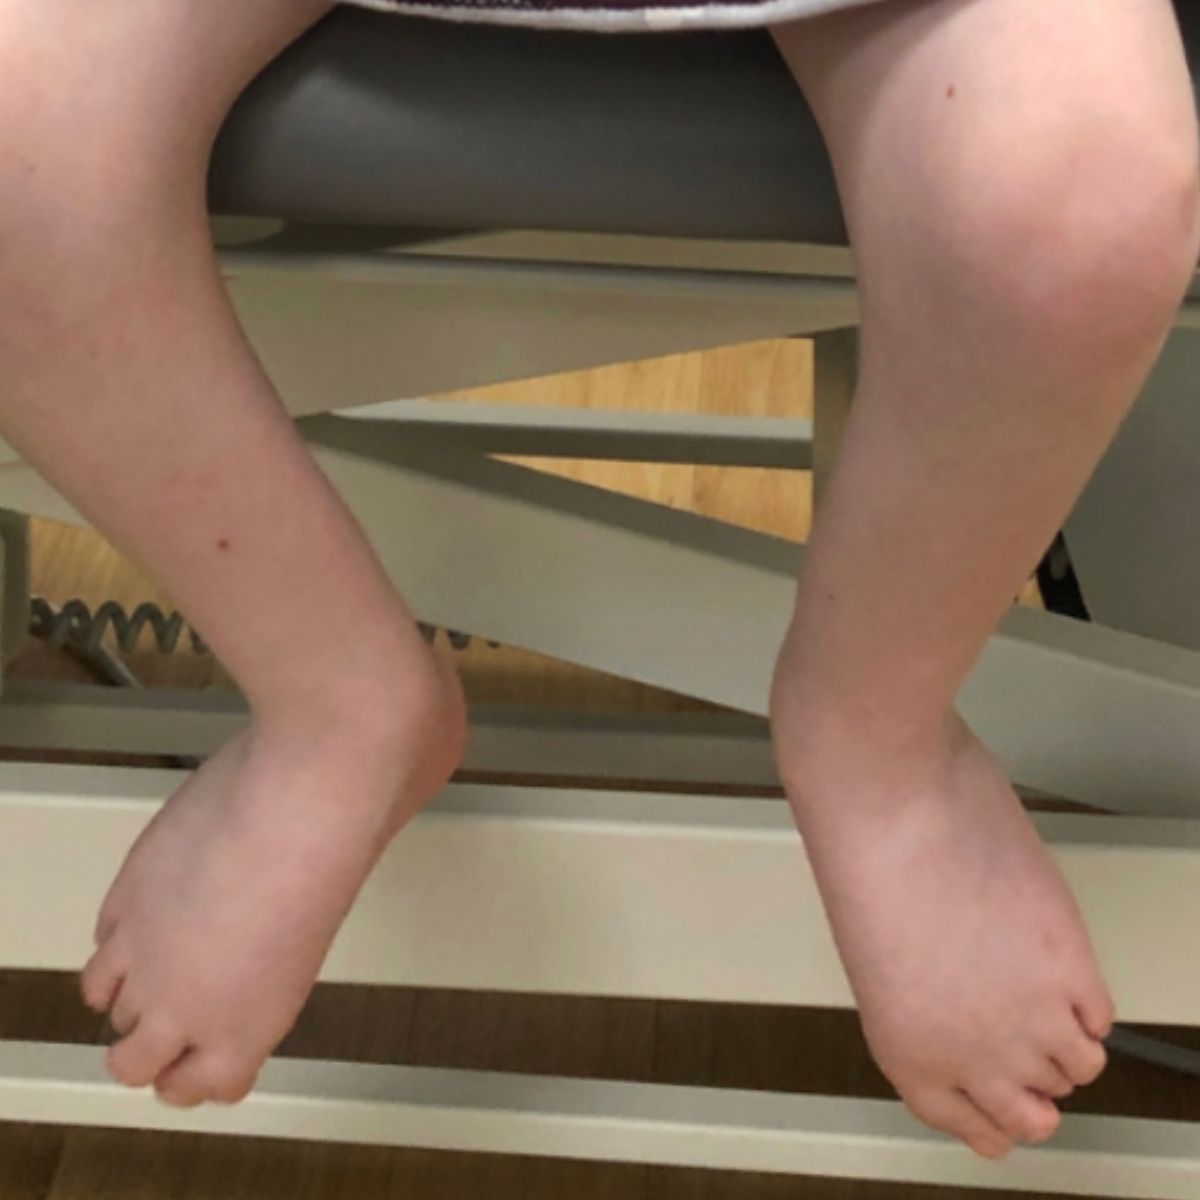
Larsen syndrome (FLNB gene mutation)
Larsen syndrome is a rare genetic disorder that affects approximately 1 in 100,000 people. It manifests from birth as dislocations of multiple joints, most commonly the hips, knees, and elbows. Clubfoot or vertical talus, as well as congenital kyphosis and scoliosis, often co-occur. The cause is usually an autosomal dominant mutation in the filamin B (FLNB) gene.
How does Larsen syndrome differ from arthrogryposis?
In arthrogryposis, the joints are stiff and the muscles are underdeveloped. In Larsen syndrome, the joints are dislocated, but the muscles are present and functional.
How do we treat Larsen syndrome?
We treat each dislocated joint separately and as early as possible, first with a cast or splint, and if necessary, with surgery—even as early as the 3rd to 6th month of life. Early reduction allows the joints to develop properly. Spinal instability requires early treatment, as it can lead to spinal cord compression if left untreated. With proper treatment, most patients walk independently and lead active lives.
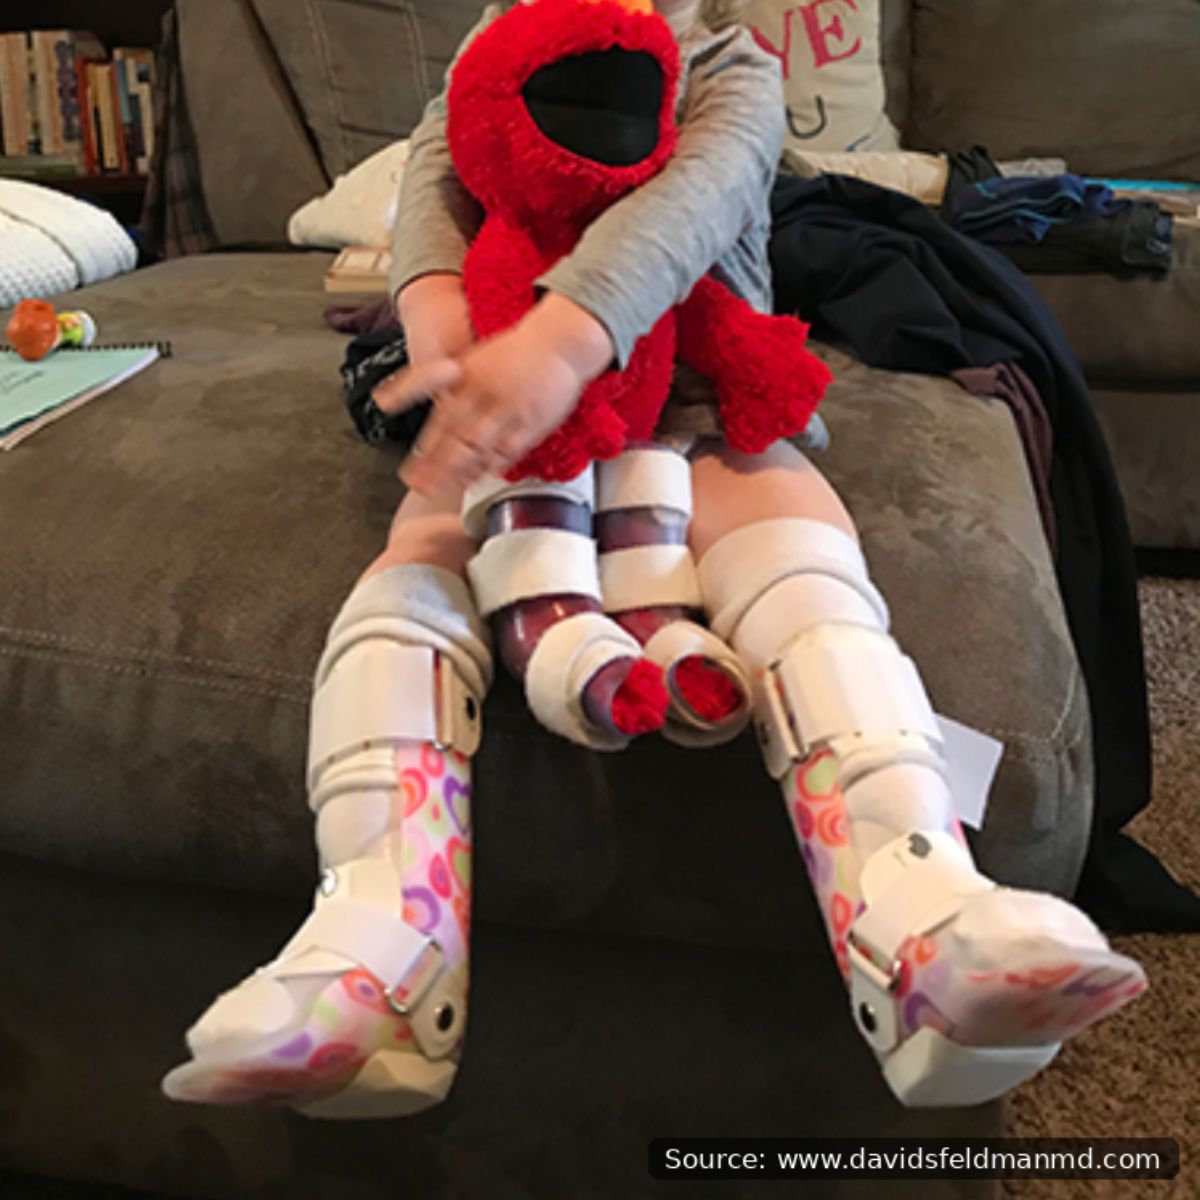
Popliteal Panniculitis Syndrome (PPS) and Escobar Syndrome
Popliteal pterygium syndrome (PPS), also known as popliteal wing syndrome, occurs in approximately 1 in 300,000 births. It is characterized by a skin fold (pterygium) behind the knee, severe flexion contracture of the knees, facial abnormalities (cleft lip or palate, lower lip fistula), syndactyly, and genitourinary abnormalities. Intellectual development is normal. Escobar syndrome is a related condition in which webbing affects multiple joints simultaneously.
Patients with PPS often walk with a crouched gait, tire easily, and have difficulty sitting. Those with severe bilateral contractures use a wheelchair to get around.
How do we treat PPS?
In the method developed by Dr. Paley, we perform extensive soft tissue release with fasciectomy (including removal of the iliotibial band), nerve decompression (sciatic, peroneal, and posterior tibial nerves), and lengthening of the hamstrings and gastrocnemius muscle. Instead of gradually stretching the joint, we shorten the femur. This allows the contracture to resolve without excessive nerve tension and with a lower risk of recurrence. We then apply a cast and use long-term orthotics.
RYR1 gene mutations
The RYR1 gene encodes the ryanodine receptor, a protein that controls skeletal muscle contraction. RYR1 mutations are one of the most common causes of congenital myopathies, including central core disease (CCD). They can cause muscle weakness, arthrogryposis-like contractures, hip dysplasia, foot deformities, and scoliosis.
Why does the RYR1 mutation require special caution?
RYR1 mutations often increase susceptibility to malignant hyperthermia. This is a potentially life-threatening reaction to certain inhalational anesthetics and muscle relaxants. In patients with the RYR1 mutation, we use anesthesia protocols that do not include these drugs (so-called “non-triggering” protocols).
How do we treat it?
We treat contractures in a similar way as in arthrogryposis, but taking into account permanent muscle weakness. Therefore, we plan surgeries more conservatively and conduct long-term, individualized physical therapy so as not to weaken the muscles that stabilize the joints. We provide treatment in collaboration with a neurologist and an orthotist.
Multimedia
Our Experts Meet the Paley European Institute Team
Family-Centered Care: treatment in which the family is part of the care team
Family-Centered Care (FCC, family-centered care) is the treatment model used at the Paley European Institute. The family of a child with a congenital limb defect is not merely an observer but a full-fledged member of the treatment team. Treatment for congenital limb defects often lasts for months or years and involves several surgeries, limb lengthening, and months of rehabilitation. Therefore, parents who understand the treatment plan and feel that their concerns are being heard have a real impact on its outcomes.
What does family-centered care look like in practice?
Parents do not wait in the hallway—while their child is undergoing surgery, the Hospital Services Coordinator and a physician’s assistant keep parents updated on the progress of the procedure via WhatsApp. During this time, a psychologist stays by the parent’s side to support them through this most difficult hour.
One treatment plan instead of multiple visits—during the consultation, specialists from various fields meet with the child in one place and develop a comprehensive treatment plan. The conversation begins not with the question “What hurts?”, but with what the child likes to do and what the family’s daily life is like.
The same physical therapist before, during, and after surgery—the therapist present in the operating room—conducts rehabilitation starting on the first day of recovery. The child exercises with someone they already know, which reduces anxiety and facilitates a return to physical fitness. This is particularly important during limb lengthening, when systematic physical therapy is crucial for maintaining joint mobility.
Comprehensive care in one place—X-rays, blood tests, an orthotist, a psychologist, a dietitian, a speech therapist, and certificates for schools and government offices—are all available without unnecessary referrals or having to search for other facilities. Surgeries are performed at our partner hospital, Medicover, where the Paley European Institute team cares for the patient from admission through discharge.
Support for families from other cities and countries—families traveling here for medical treatment receive assistance with arranging transportation, accommodations, and all the logistics of their stay.
Parents' Council—parents who have themselves undergone treatment at the Paley European Institute—regularly test and evaluate new approaches, helping to shape the model of care.
Why does family involvement improve treatment outcomes?
Parents who understand the treatment plan are better able to follow rehabilitation recommendations at home and recognize signs that require contacting a doctor more quickly. Thanks to preparing the family for home care, children who undergo surgery at the Paley European Institute stay in the hospital for an average of only 2 days. A shorter hospital stay and less stress lead to a more peaceful recovery and a better quality of life for the entire family.

Related articles
Read the blog posts on this topic

Arthrogryposis - Causes, symptoms and treatment
Arthrogryposis - are there effective treatments for joint stiffness?

June 30 - World Arthrogryposis Day

Arthrogryposis treatment at Paley European Institute - Arabella's story

World Arthrogryposis Day
Your most frequently asked questions
Here's what you should know before making a decision.
No. The most common form, amyoplasia, is usually not hereditary. Many other forms, however—especially distal arthrogryposis—have a genetic basis.
Most commonly, a panel of genes associated with arthrogryposis and myopathies (NGS) or whole-exome sequencing (WES). These tests are ordered and interpreted by a clinical geneticist.
No. Some mutations are difficult to detect. The diagnosis is based on a combination of clinical presentation and test results.
It depends on the mode of inheritance. The risk is usually 50% for dominant inheritance and 25% for recessive inheritance. De novo mutations rarely recur. A geneticist assesses the risk for a specific family.
Yes, if the anesthesiologist is aware of the mutation and follows a protocol that excludes drugs that can cause malignant hyperthermia. The test results must always be reported before the procedure.
The mutation cannot be removed, but its effects on the musculoskeletal system (contractures, dislocations, deformities) can be treated conservatively or surgically. Many patients are able to walk independently.
From the first weeks of life. In Larsen syndrome, surgical joint reduction may be necessary as early as the first six months.