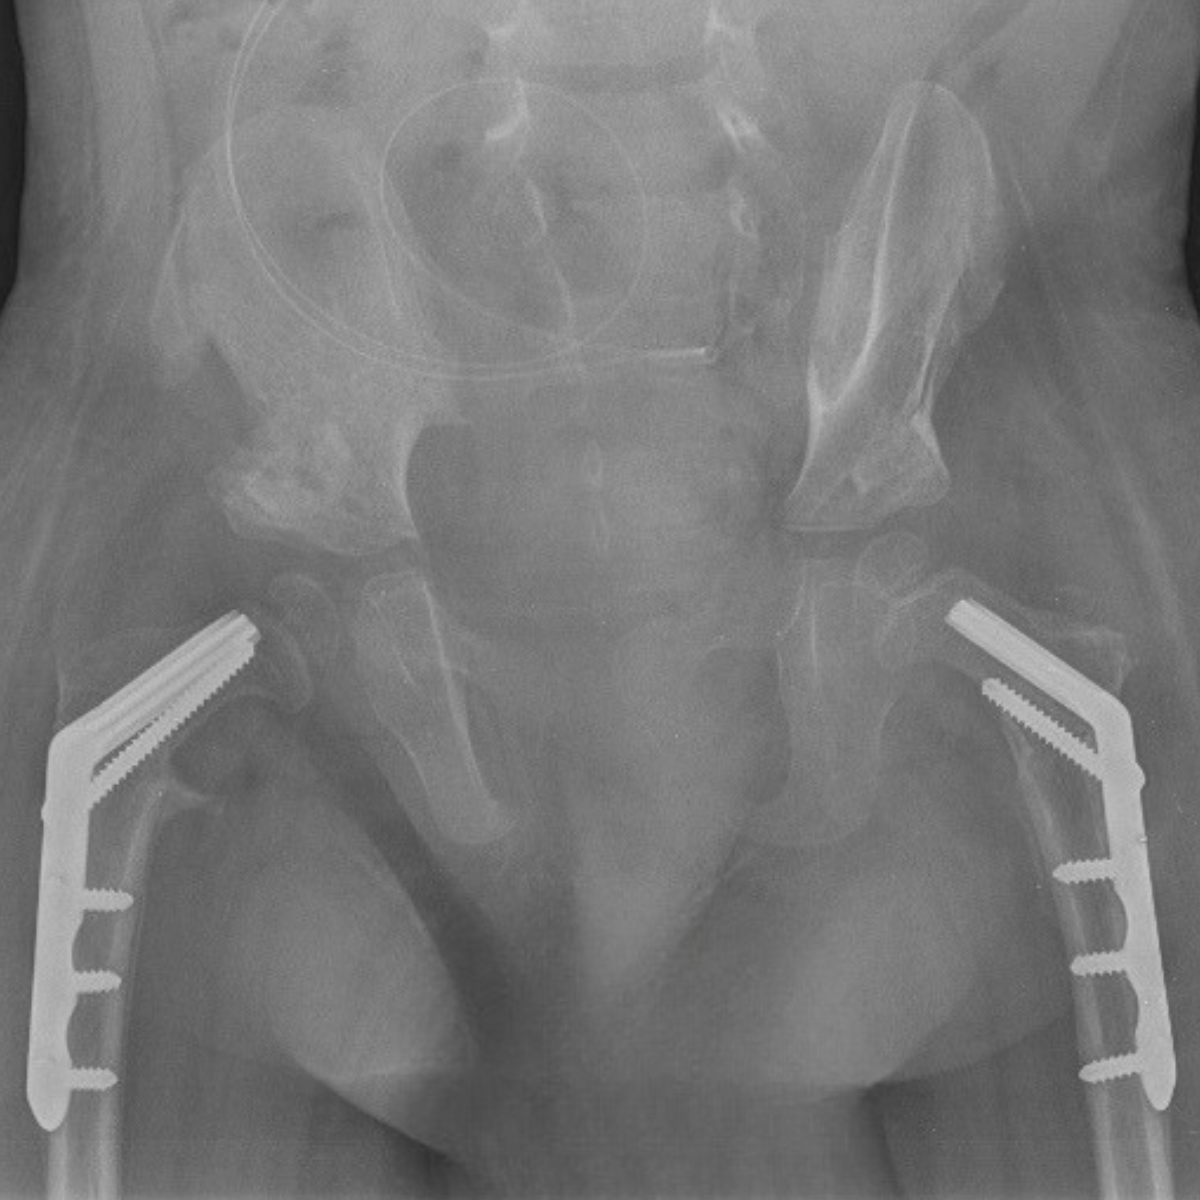
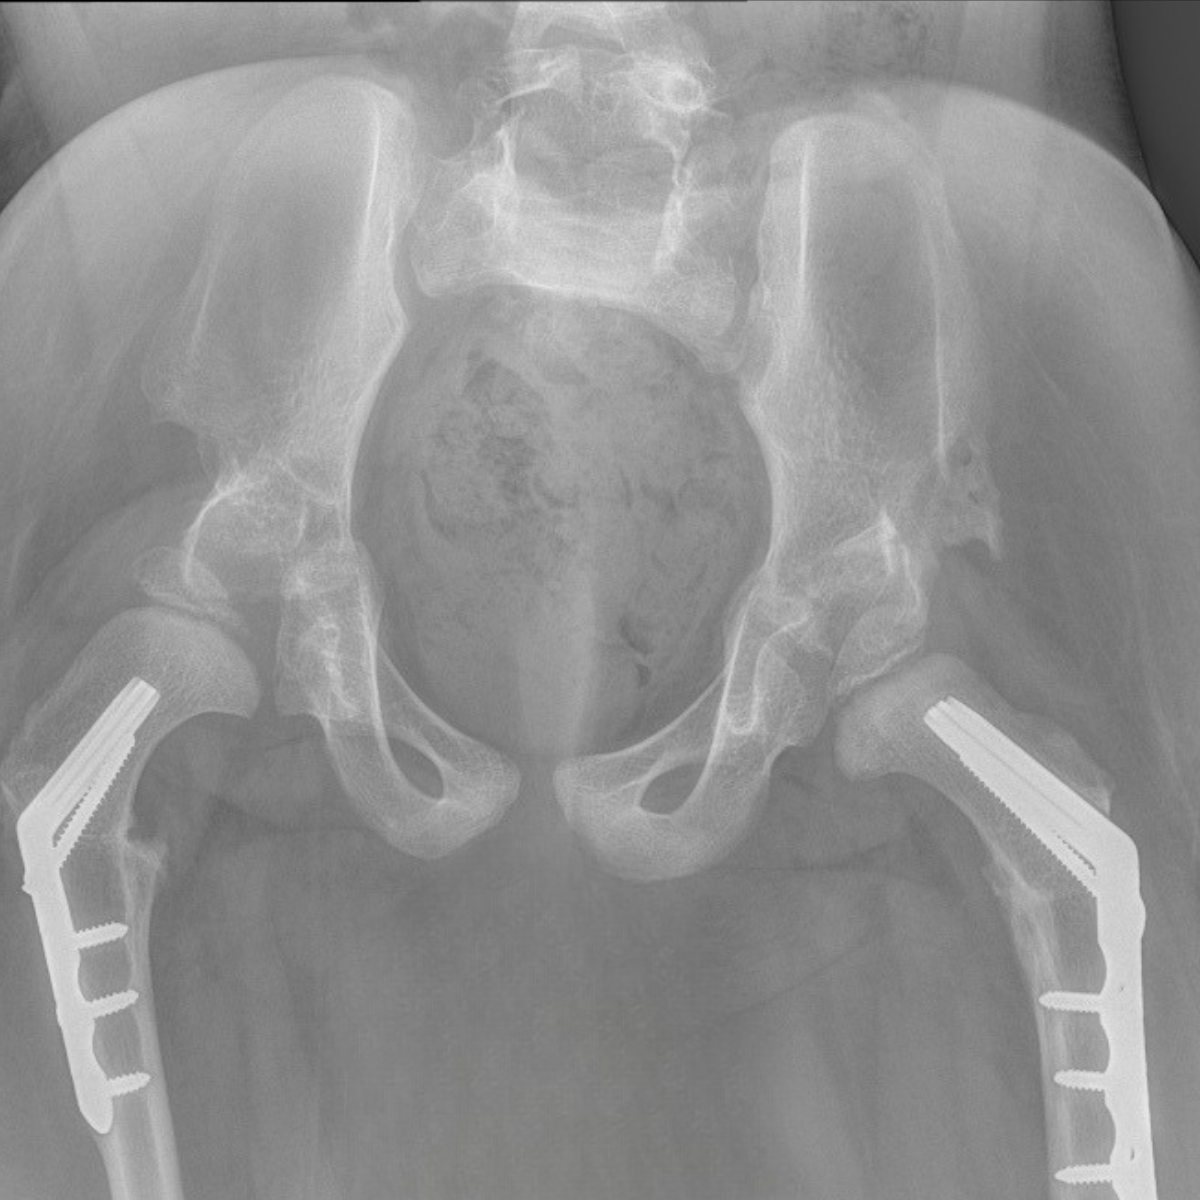
Neuromuscular Disorders – Neuro-Orthopedic Treatment for Children and Adults
At the Paley European Institute, we treat neuromuscular disorders—such as cerebral palsy (CP), spina bifida, and spinal muscular atrophy (SMA)—using a multilevel orthopedic approach. Instead of surgically correcting individual contractures over the course of several years, we plan to correct the entire limb and the entire movement pattern as part of a single treatment strategy. The goal is to reduce pain, improve gait or sitting stability, and increase the patient’s independence.
What are neuromuscular disorders?
Neuromuscular disorders are a group of conditions in which damage to the nervous system (the brain, spinal cord, or peripheral nerves) or to the muscles themselves disrupts muscle tone, strength, and coordination of movement. Over time, this leads to contractures, bone and joint deformities, and problems with walking, sitting, and posture.
The neurological condition itself often does not progress, but its effects on the musculoskeletal system become more pronounced as the child grows. That is why early and regular orthopedic care is so important.
The Most Common Neuromuscular Disorders Treated Orthopedically
spina bifida (meningo-spinal hernia)
spinal muscular atrophy (SMA)
Familial (hereditary) spastic paraparesis (HSP)
Neuromuscular disorders
Reasons
damage to the developing brain before, during, or shortly after birth, such as due to hypoxia, bleeding, or preterm birth (MPD)
neural tube defects (spina bifida)
genetic mutations: in the SMN1 gene in SMA, in the MECP2 gene in
Rett syndrome and hereditary mutations in HSP
factors during pregnancy, such as infections, certain medications, or the mother's diabetes
Symptoms
The most important symptom is abnormal muscle tone: increased (hypertonia, or spasticity or stiffness) or decreased (hypotonia, or flaccidity). Other symptoms include: delayed motor development, walking on tiptoes, a scissor gait, or a gait with bent knees; joint contractures and limited range of motion; hip pain; limping; difficulty sitting; scoliosis; and foot deformities
Diagnostics
A neurologist diagnoses the underlying condition based on a physical examination, MRI, EMG, or genetic testing. An orthopedist assesses its effects on the musculoskeletal system: range of motion in the joints and contractures, alignment of the hips, knees, and feet, as well as the spine (X-ray), and gait pattern using computerized gait analysis, which is a standard diagnostic tool at the Paley European Institute
When should you see an orthopedist for a neuromuscular disorder?
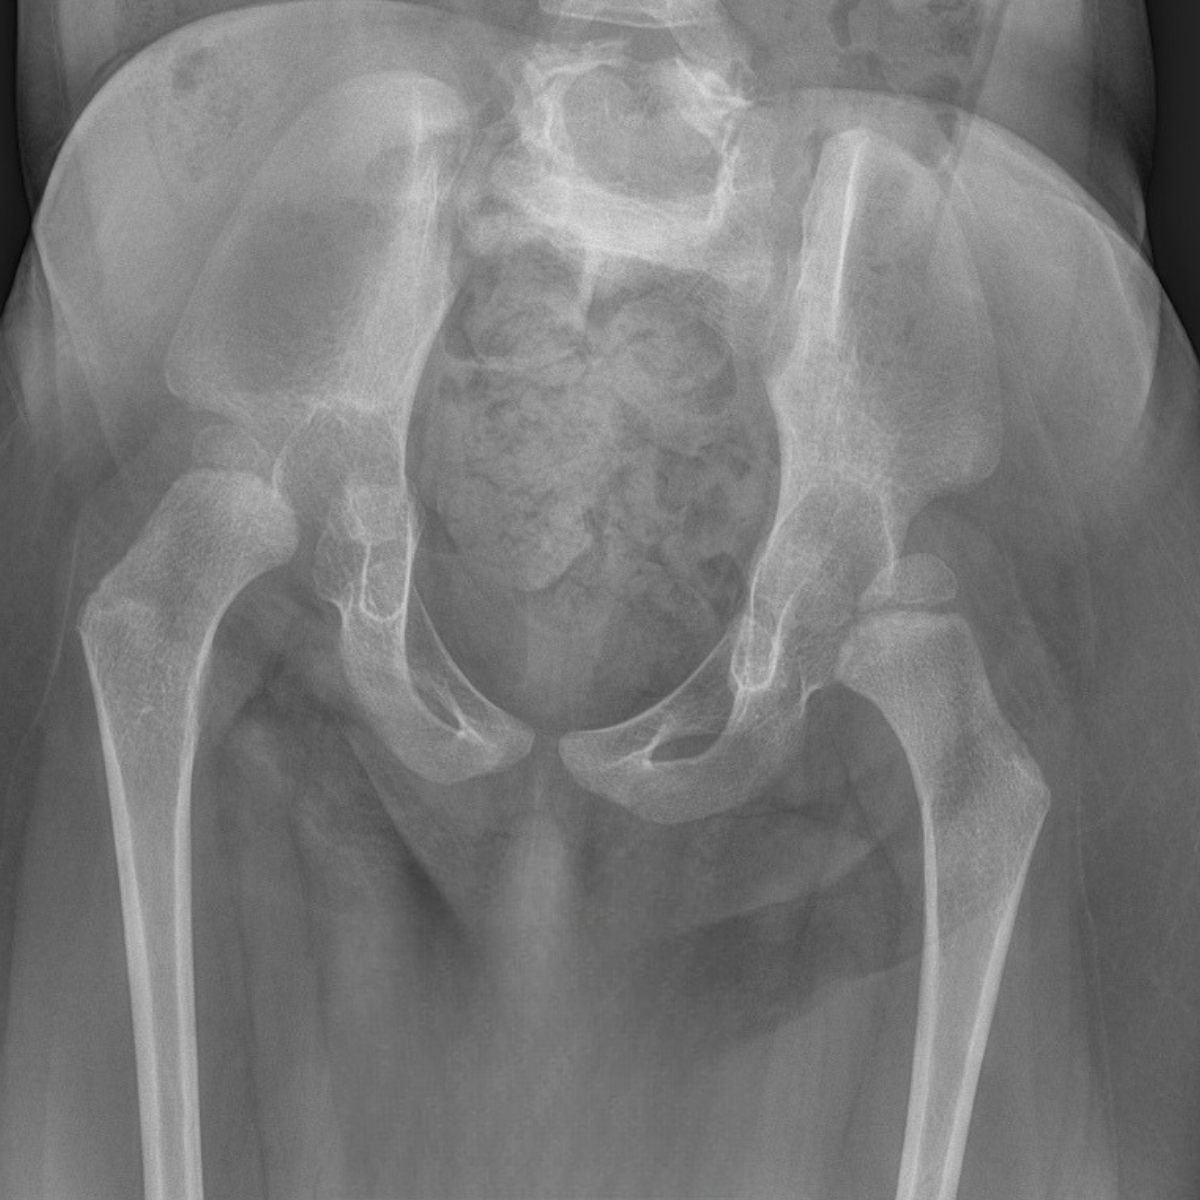
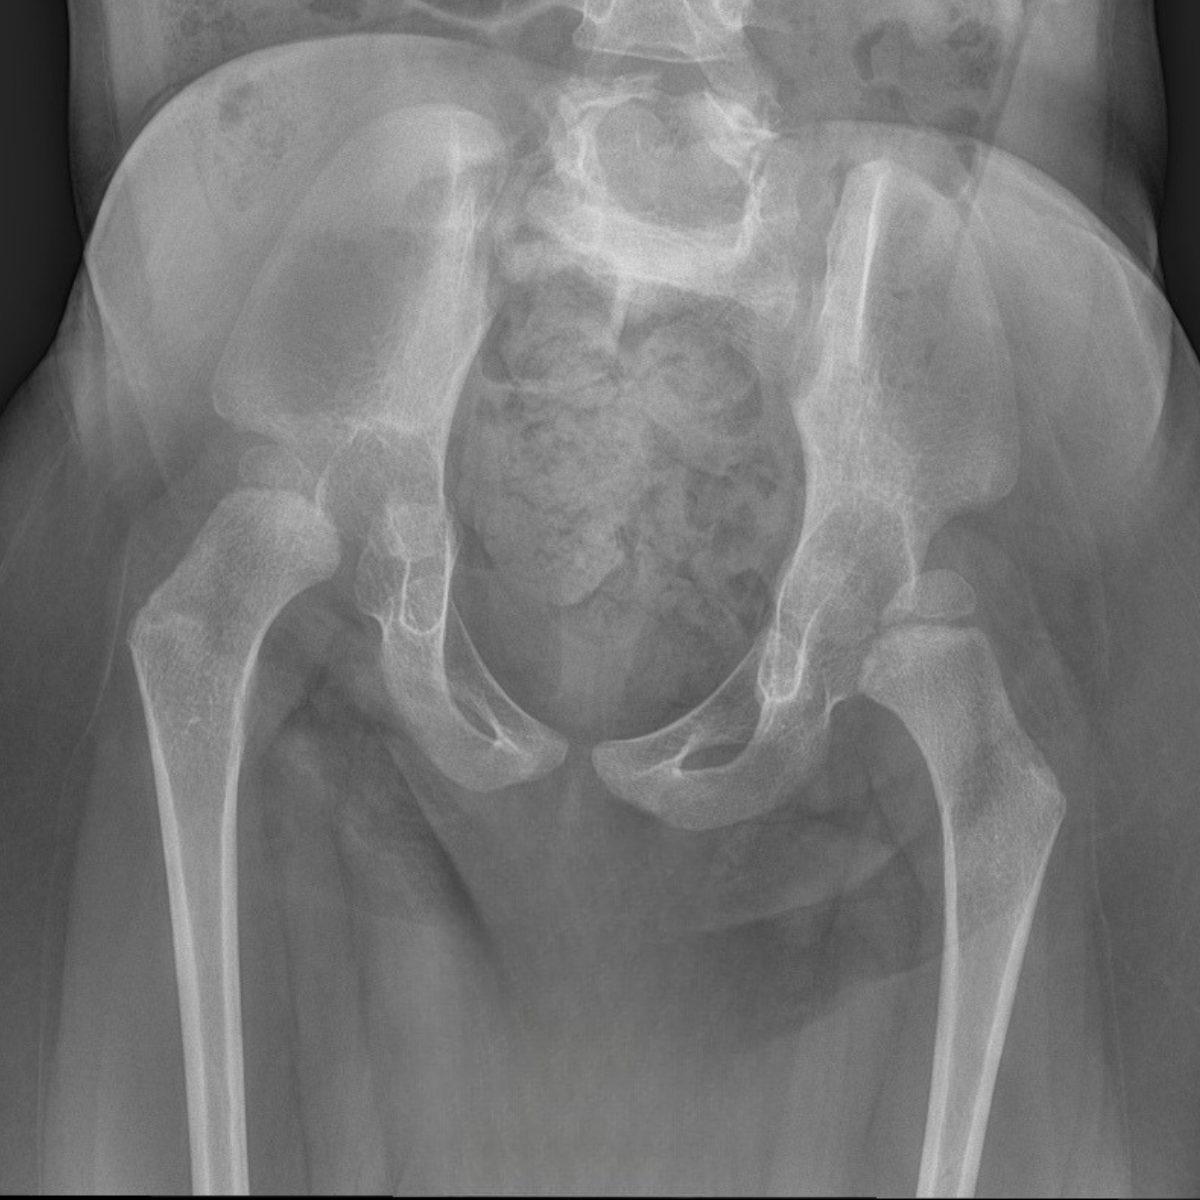
It is advisable to see an orthopedist immediately after a neurological condition is diagnosed, before permanent contractures and deformities develop. For children with cerebral palsy, regular X-ray follow-ups of the hips are recommended, because hip subluxation may be asymptomatic for a long time, and when detected early, it can be treated with less invasive methods.
A consultation is particularly recommended when:
The child walks on tiptoes, with bent knees, or crosses their legs while walking
hip pain, limping, or difficulty sitting have developed
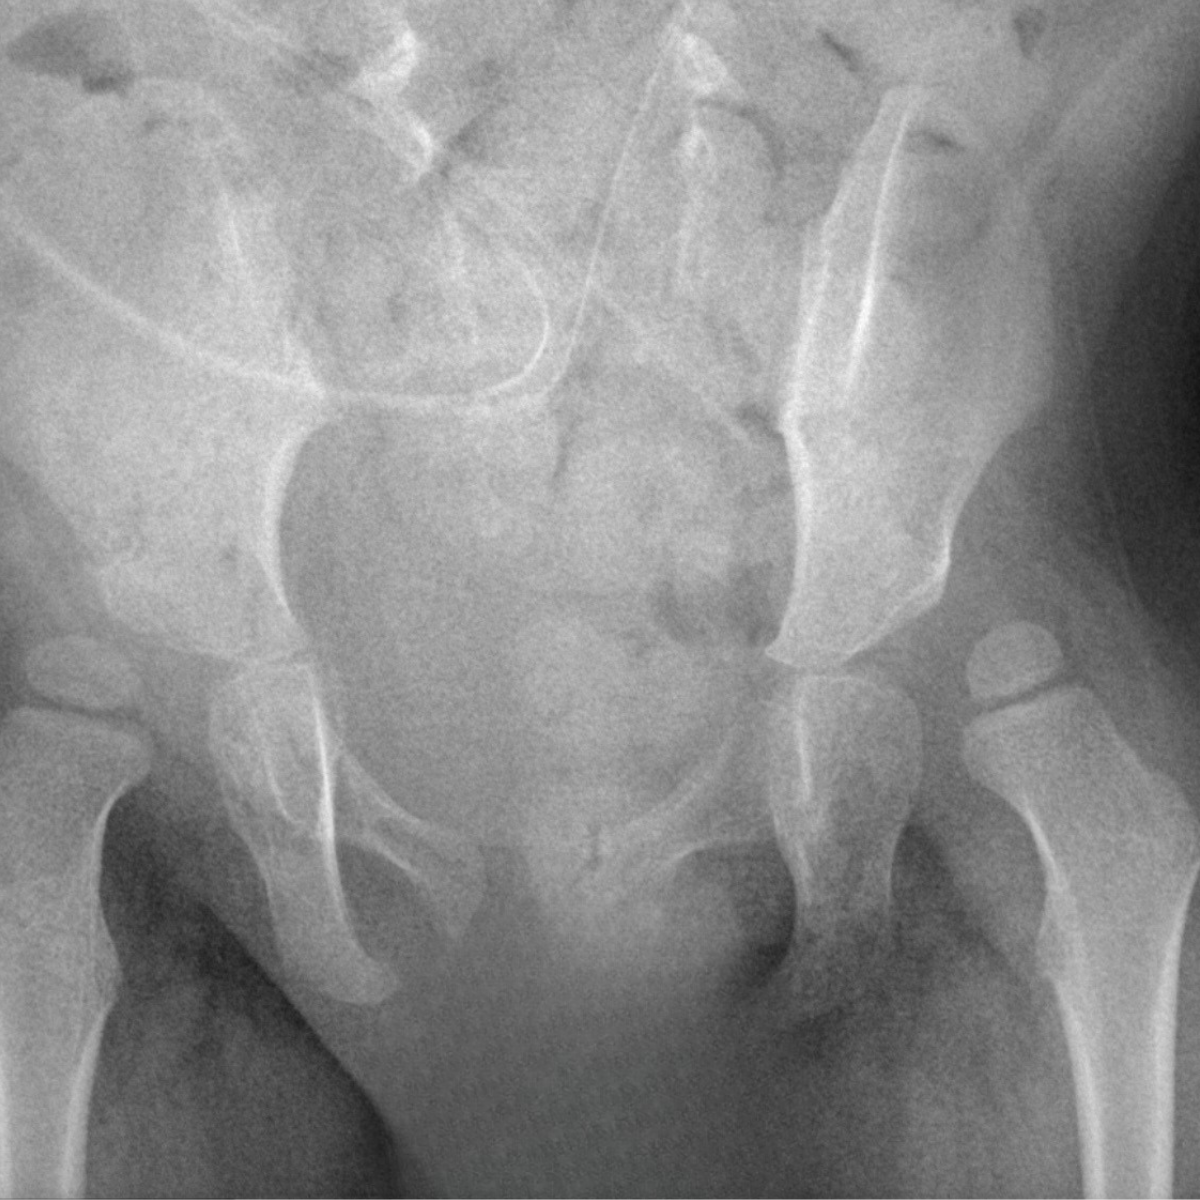
An X-ray revealed a subluxation or dislocation of the hip joint
Contractures are worsening despite rehabilitation
The feet are misaligned, making it difficult to find the right orthotics
A spinal curvature or pelvic asymmetry is visible
The child loses previously acquired motor skills
After neurosurgical treatment (e.g., SDR), contractures remained that limited walking

How do we treat neuromuscular disorders?
We tailor treatment to each patient’s specific condition, age, functional ability, and goals, as well as those of their family. This includes diagnostics, muscle tone management, minimally invasive treatments, multilevel surgeries, and hip reconstructions, as well as physical therapy and orthopedic devices.
Diagnosis and qualification
orthopedic examination and assessment of joint range of motion
X-rays of the hips, spine, and limbs
computer-based gait analysis
assessment of functional potential and establishment of treatment goals
Muscle Tone Assessment
Multilevel administration of botulinum toxin under sedation
Routine casting to reduce contractures
A delordotic corset for hip flexion contracture
Minimally invasive treatment
Percutaneous muscle lengthening using the PERCS and SPML methods
Stretching several muscles during a single session
Surgical treatment
Bilateral hip replacement without a cast
SEMLS multilevel surgeries (hip, knee, and foot in a single procedure)
Osteotomies to correct limb alignment and corrections of foot deformities
Rehabilitation and Long-Term Care
Physical therapy starting the day after hip surgery
learning proper movement patterns, strength and balance exercises
Selection of Orthoses and Assistive Devices
regular checkups, including postoperative gait analysis
What challenges do patients with neuromuscular disorders face?
Patients and their families are primarily faced with the fact that musculoskeletal problems worsen with age and affect their independence, even if the neurological disease itself does not progress.
Progressive contractures: Abnormal muscle tension continuously shortens the muscles, which cannot keep up with bone growth.
Hip Instability: Uneven pulling by spastic muscles pulls the head of the femur out of the acetabulum, leading to subluxation, dislocation, and pain.
Abnormal gait: Walking on tiptoes, with bent knees, or in a scissor-like pattern increases energy expenditure and the risk of falls.
Scoliosis. Weak trunk muscles fail to stabilize the spine, making it difficult to sit and, in cases of severe curvature, also to breathe.
Multiple surgeries in the coming years: Correcting problems one by one means multiple anesthesias, hospitalizations, and interruptions in rehabilitation.
That is why we take a multi-level approach: we address all significant issues at the same time and provide a single, intensive rehabilitation program.
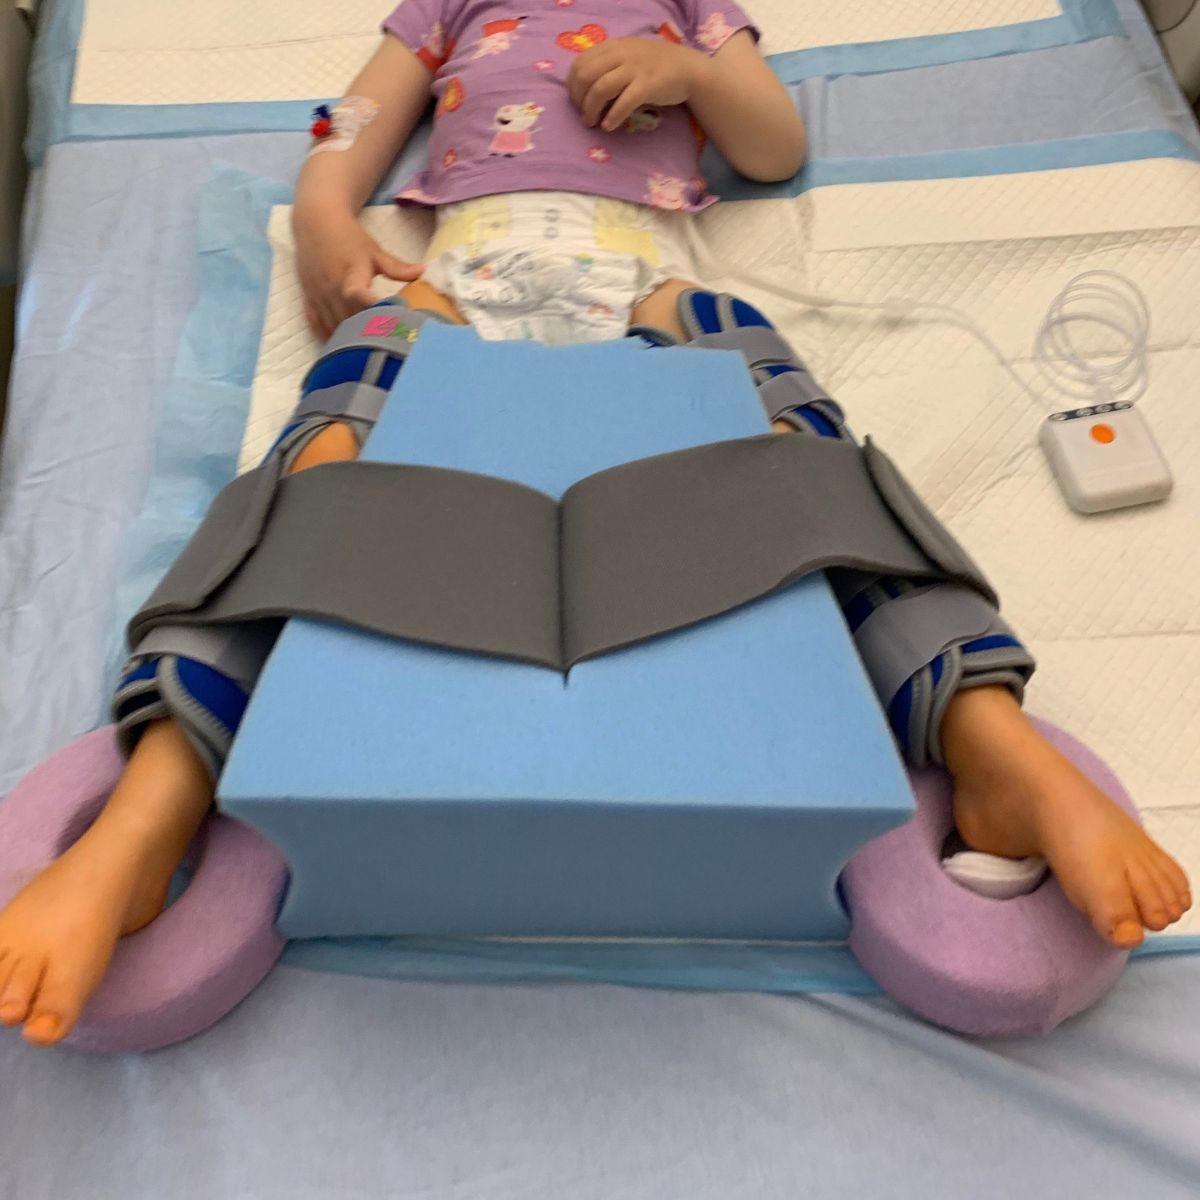
Cerebral Palsy (CP)
Cerebral palsy is a non-progressive injury to the developing brain that occurs before, during, or shortly after birth. The most common causes include prematurity, hypoxia, intracranial hemorrhage, and infections. Cerebral palsy affects muscle tone, posture, balance, and coordination. The most common form is spastic cerebral palsy, in which the muscles are constantly tense and shortened. The brain damage itself does not worsen, but its effects on the musculoskeletal system increase as the child grows: contractures, hip subluxations, foot deformities, and gait abnormalities develop.
Diagnosis
MPD is diagnosed by a neurologist based on an examination of the child, the history of the pregnancy and delivery, and a brain MRI. An orthopedist assesses the effects of the condition on the musculoskeletal system: range of motion in the joints, contractures, and the alignment of the hips, knees, feet, and spine. Regular hip X-rays are recommended for children with MPD, as subluxation often remains asymptomatic for a long time. At the Paley European Institute, computerized gait analysis is standard practice; it identifies which muscles and joints are impairing movement.
Our Approach to Treatment
We treat MPD using a multilevel orthopedic approach. Instead of correcting individual contractures year after year, we plan treatment for the entire limb and the entire movement pattern. Each treatment plan is tailored individually, based on the child’s functional ability, gait analysis, and the family’s goals.
Treatment methods:
Multilevel administration of botulinum toxin under sedation reduces spasticity in multiple muscles simultaneously, including the iliopsoas muscle.
Regular casting and a delordotic brace—gradually reduce contractures.
PERCS and SPML – minimally invasive, percutaneous muscle lengthening, including in children who have undergone rhizotomy (SDR).
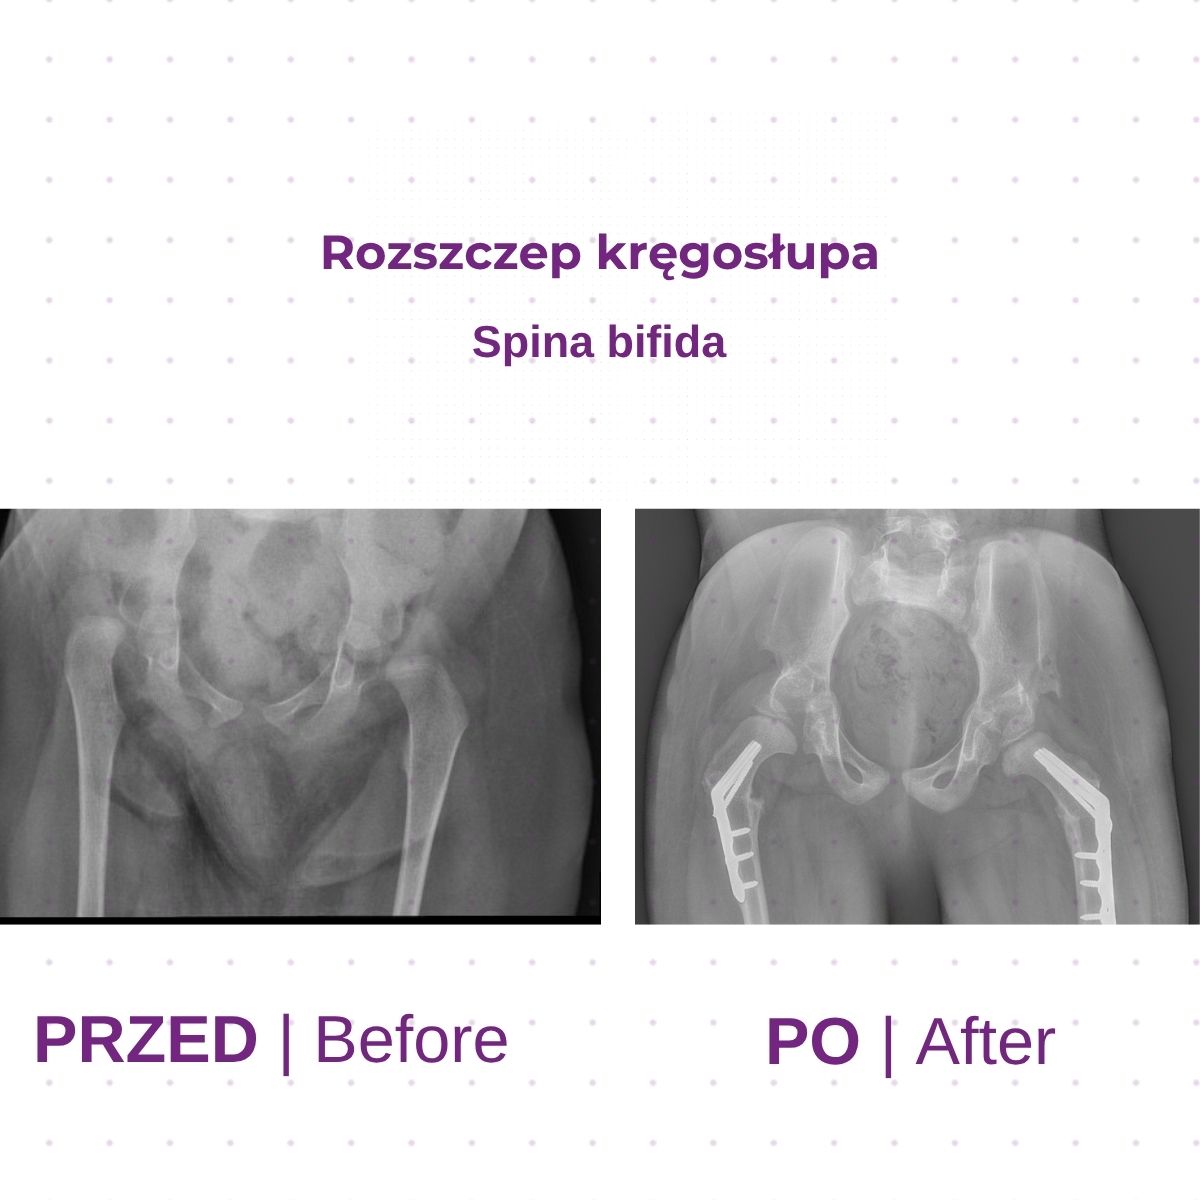
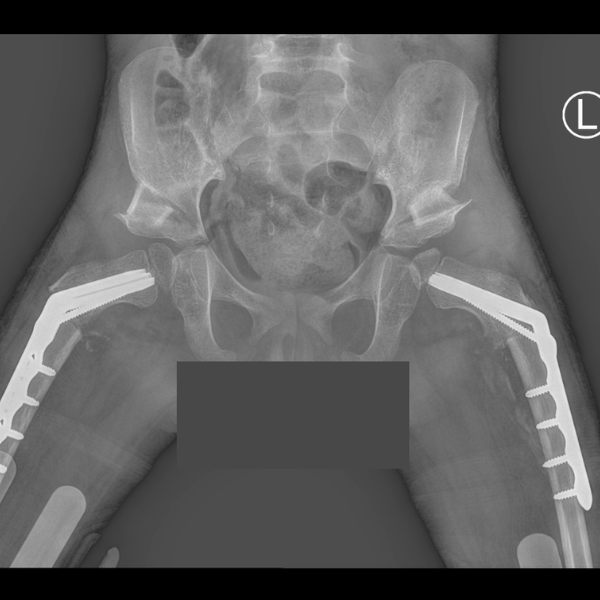
Bilateral hip replacement without a cast—both hips in a single procedure, with a triple pelvic osteotomy (tPAO).
SEMLS Multilevel Surgery – Hip, Knee, and Foot Correction Under a Single Anesthesia.
Post-operative care
After hip reconstruction, the child does not have a cast, and we begin rehabilitation the very next day. The hospital stay usually lasts 3–4 days, and a parent may stay with the child the entire time. Following SEMLS, we implement an individualized rehabilitation program: teaching proper movement patterns, strength and balance exercises, fitting orthoses, and postoperative gait analysis.
Treatment Outcomes
Multilevel treatment improves gait patterns, reduces contractures and pain, and increases the child’s independence. Over the past five years, the hips have remained stable in 97% of patients who underwent surgery, with no need for repeat surgery. Correcting all issues at once also reduces the number of future surgeries.

Spina bifida
Spina bifida is a congenital neural tube defect in which the spinal canal does not close properly during the first weeks of pregnancy. The most severe and common form is myelomeningocele (MMC), in which the spinal cord is damaged. This results in sensory disturbances, flaccid or spastic paralysis of the lower limbs, bladder and bowel problems, and deformities of the feet, knees, hips, and spine. Hydrocephalus and Arnold-Chiari syndrome often co-occur. The higher up the defect is located, the greater the mobility limitations.
Diagnosis
Spina bifida is often detected during pregnancy via ultrasound. After birth, a neurosurgeon closes the defect, and a team of specialists takes over further care. An orthopedist determines the level of paralysis, assesses muscle strength, range of motion, and the alignment of the feet, hips, and spine, as well as the patient’s ability to stand upright and walk.
Our Approach to Treatment
The goal of orthopedic treatment is to maximize the patient’s independence: standing, walking with orthoses, or sitting stably and comfortably in a wheelchair. We tailor the treatment plan to the severity of the condition and the child’s mobility.
Treatment methods:
Physical therapy—maintaining range of motion, strengthening remaining muscles, and learning to stand upright.
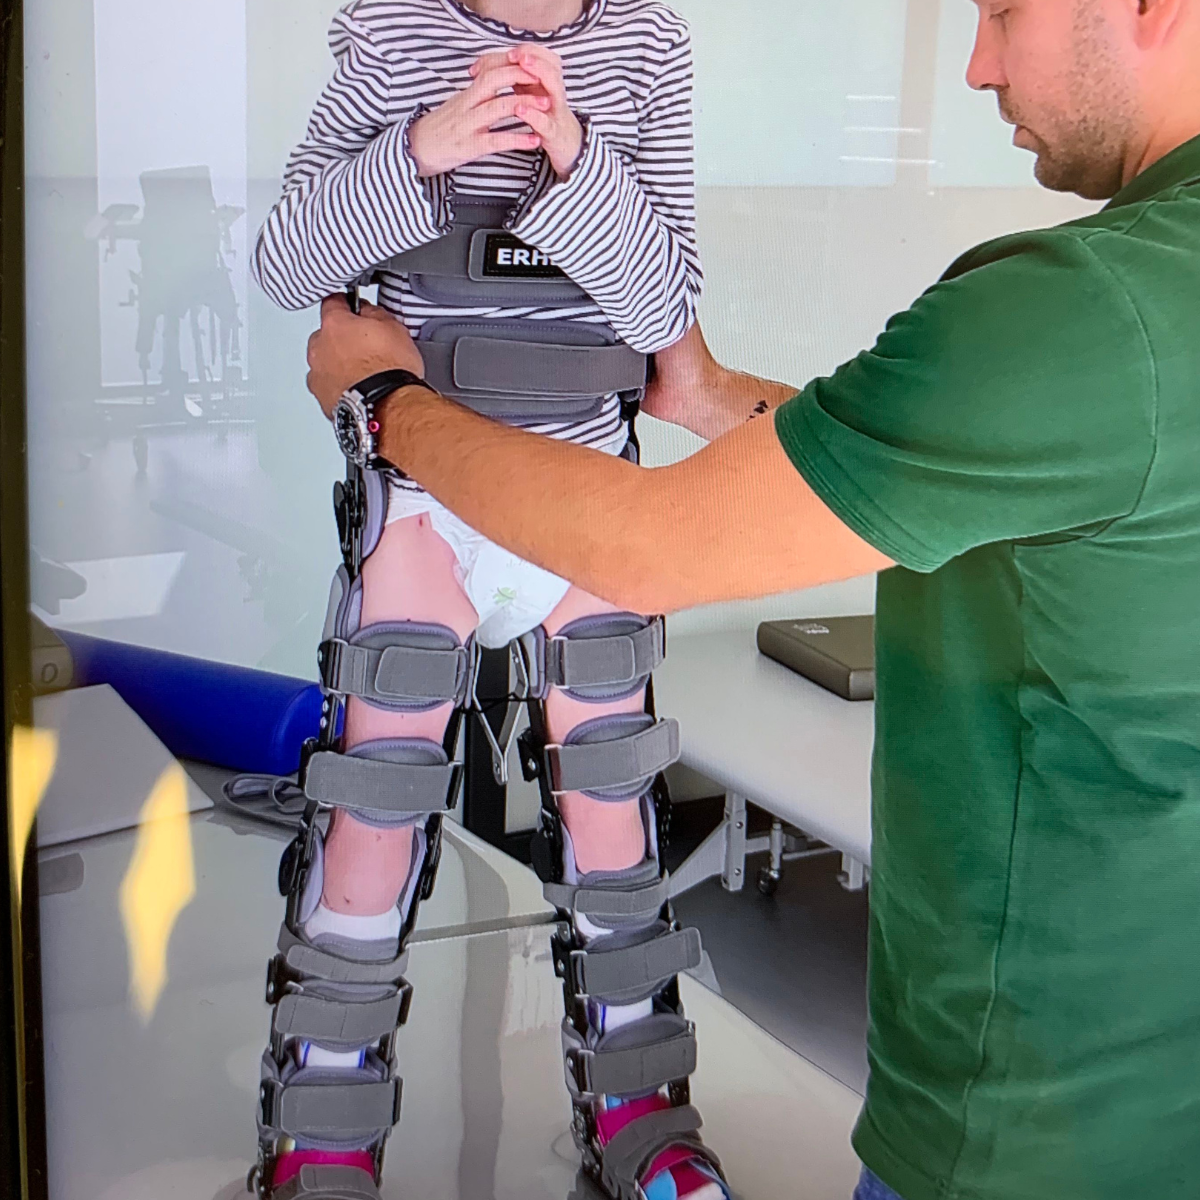
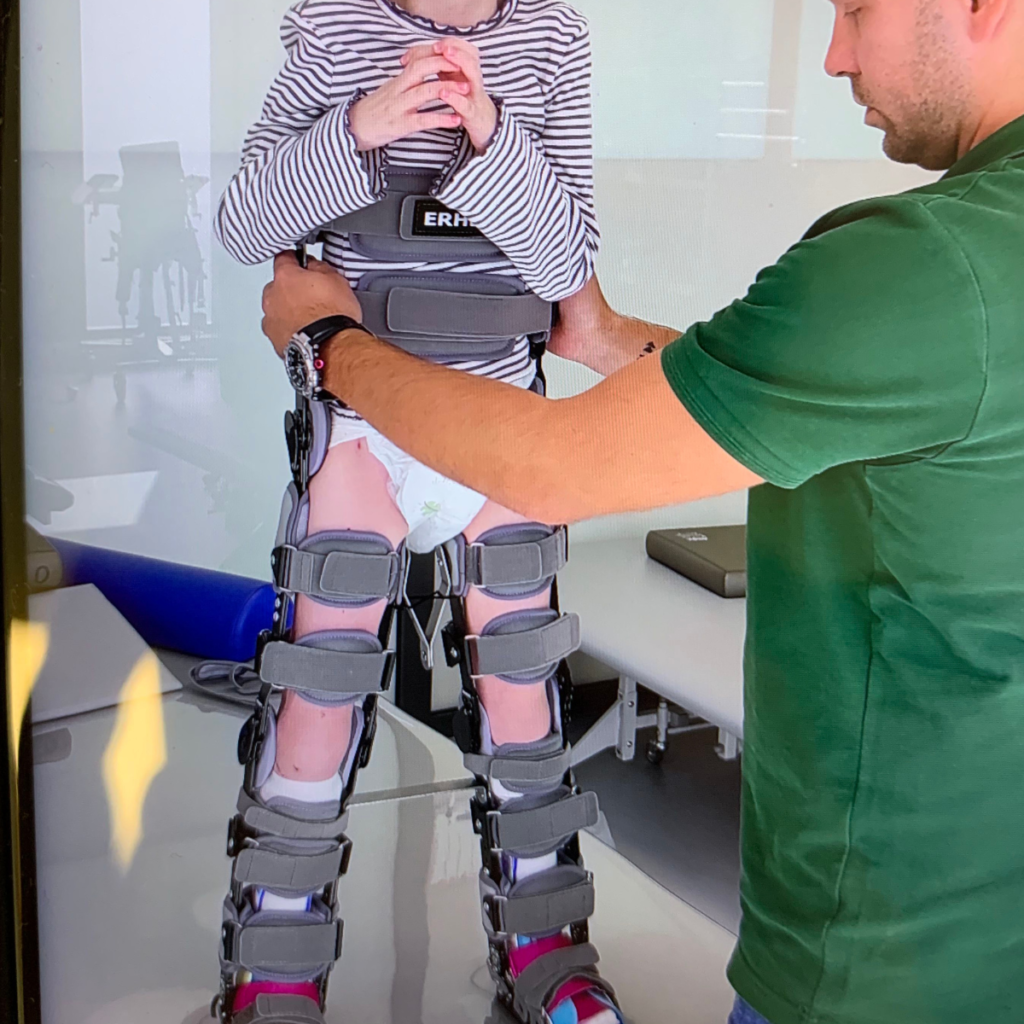
Braces and orthotics – joint stabilization, enabling standing and walking.
Releasing contractures—in the hips, knees, and ankles.
Correction of foot deformities—to ensure the foot is flat and fits properly in the orthosis.
Multilevel surgeries and osteotomies—correction of limb alignment in selected patients.
Post-operative care
After surgery, we provide rehabilitation focused on regaining the ability to stand and walk or to sit comfortably. We select new orthoses and equipment. Due to sensory disturbances, we teach parents how to care for their child’s skin and prevent pressure sores and chafing.
Treatment Outcomes
When properly managed, orthopedic treatment allows many patients to walk with orthoses or move independently in a wheelchair. Correcting contractures and deformities facilitates standing, reduces the risk of pressure sores, and improves the quality of daily life.

Spinal Muscular Atrophy (SMA)
Spinal muscular atrophy (SMA) is a genetic neuromuscular disorder caused by a mutation in the SMN1 gene. Motor neurons in the spinal cord gradually die off, leading to muscle weakness and wasting, particularly in the trunk and limbs. There are several types of SMA, ranging from the most severe type 1 in infants to the milder type 3, in which children usually begin to walk. Thanks to gene therapies and disease-modifying drugs, patients with SMA live longer and are more functional than in the past, but they still often have significant mobility limitations.
Diagnosis
SMA is confirmed by genetic testing. In Poland, newborns are screened for SMA as part of routine newborn screening. An orthopedist regularly evaluates the spine (X-ray), hip joints, range of motion, and contractures to detect scoliosis and hip instability early.
Our Approach to Treatment
A neurologist oversees medication management, and our role is to protect the musculoskeletal system. Scoliosis develops in nearly all patients with SMA types 1 and 2 and in about half of those with type 3, which is why regular checkups and early intervention are crucial. We make every decision regarding surgical treatment with caution, after assessing the patient’s respiratory function and overall health.
Treatment methods:
Physical Therapy – maintaining range of motion, preventing contractures, aquatic therapy.
Braces and seat supports—they slow the progression of scoliosis and improve sitting stability.
Braces and standing frames—maintaining proper limb alignment.
Treatment of contractures—release of soft tissues in the hip and knee regions.
Treatment of hip instability—reconstruction when a dislocation causes pain, results in a tilted pelvis, or makes sitting difficult.
Post-operative care
After the procedure, we work closely with a neurologist and a pulmonologist, because patients with SMA have weaker respiratory muscles. Rehabilitation is gentle and tailored to the patient’s strength. We select new seating solutions and equipment, and teach the family how to position the child properly.
Treatment Outcomes
Orthopedic care helps patients maintain mobility, a stable sitting position, and the freedom to use their hands for longer. Controlling scoliosis also protects respiratory function, and treating contractures and hip issues makes daily self-care easier.
Rett syndrome
Rett syndrome is a rare, genetic neurodevelopmental disorder that affects almost exclusively girls. It is most commonly caused by a mutation in the MECP2 gene on the X chromosome and occurs in approximately 1 in 10,000–23,000 girls born. Initially, the child develops normally, but between 6 and 18 months of age, regression sets in: loss of acquired skills, especially purposeful hand movements, speech, and often walking. Characteristic features include stereotypical hand movements (e.g., rubbing, clapping), slowed head growth, balance and breathing disorders, and epilepsy. As the child gets older, scoliosis, contractures, and foot deformities often develop.
Diagnosis
The diagnosis is based on clinical observation and the child’s developmental history, and it is crucial to identify a regression following a period of normal development. The diagnosis is confirmed by genetic testing for the MECP2 mutation. Tests such as an EEG or MRI help rule out other conditions and assess any comorbidities. An orthopedist regularly monitors the spine, hips, and feet.
Our Approach to Treatment
At the Paley European Institute, we focus on the orthopedic aspects of care for patients with Rett syndrome, working in collaboration with a neurologist and physical therapists. Our goal is to preserve the ability to walk and maintain stable posture for as long as possible, and to improve the quality of life for the child and their family.
Treatment Methods for
There is no curative treatment, so treatment is symptomatic and supportive:
Physical Therapy – maintaining motor function, preventing contractures.
Braces and orthotics – posture stabilization and gait assistance.
Botulinum toxin and muscle lengthening—reducing contractures.
Surgical treatment of deformities—foot correction, treatment of hip subluxations.
Spinal Checkups – Regular X-rays and Braces for Scoliosis.
Post-operative care
After the procedure, we provide rehabilitation aimed at helping patients return to their pre-surgery level of fitness as quickly as possible. We help patients select the appropriate equipment and orthoses, and we provide families with information and support at every stage of treatment.
Treatment Outcomes
Appropriately tailored treatment and early intervention can prolong the period of independent walking, reduce the number of orthopedic complications, and make daily care for the child easier.
Familial spastic paraparesis (HSP, hereditary spastic paraplegia)
Familial spastic paraparesis (HSP, hereditary spastic paraplegia) is a group of hereditary disorders in which the nerve pathways that carry signals from the brain to the leg muscles are gradually damaged. This results in slowly progressive spasticity and weakness in the lower limbs. The first symptoms may appear in childhood or in adulthood. Typical symptoms include walking on tiptoes, stiff legs, stumbling, and difficulty maintaining balance. Over time, the Achilles tendons and the hamstring muscles shorten.
Diagnosis
HSP is diagnosed by a neurologist based on symptoms, family history, magnetic resonance imaging (MRI), and genetic testing, which help rule out other conditions. In childhood, HSP is sometimes mistaken for a mild form of MPD. An orthopedist evaluates contractures, the alignment of the feet and knees, and gait, including through computerized gait analysis.
Our Approach to Treatment
The disease progresses slowly, so we plan treatment with the goal of maintaining the ability to walk over the long term. We take a step-by-step approach: first, we use conservative and minimally invasive methods, and we resort to surgery only when contractures or deformities significantly limit mobility.
Treatment methods:
Physical therapy—stretching, muscle strengthening, balance exercises.
Botulinum toxin – temporary reduction in spasticity.
PERCS and SPML – minimally invasive muscle lengthening.
Stretching the tendons—including the Achilles tendon—while walking on tiptoes.
Corrective osteotomies – improvement of limb alignment.
Braces – Ankle Stabilization.
Post-operative care
After the procedure, we provide rehabilitation focused on restoring strength, balance, and a proper gait pattern.
We monitor progress, including gait analysis, and select orthoses.
Treatment Outcomes
Treatment will not stop the disease, but it reduces contractures, improves balance and gait, and helps patients maintain their ability to move independently for longer.

Multimedia
Scientific Articles: Neuromuscular Disorders
Our Experts Meet the Paley European Institute Team
Family-Centered Care: treatment in which the family is part of the care team
Family-Centered Care (FCC, family-centered care) is the treatment model used at the Paley European Institute. The family of a child with a congenital limb defect is not merely an observer but a full-fledged member of the treatment team. Treatment for congenital limb defects often lasts for months or years and involves several surgeries, limb lengthening, and months of rehabilitation. Therefore, parents who understand the treatment plan and feel that their concerns are being heard have a real impact on its outcomes.
What does family-centered care look like in practice?
Parents do not wait in the hallway while their child is undergoing surgery—the Hospital Services Coordinator and the physician’s assistant keep parents updated on the progress of the procedure via WhatsApp. During this time, a psychologist stays by the parent’s side to support them through this most difficult hour.
One treatment plan instead of multiple visits —during the consultation, specialists from various fields meet with the child in one place and develop a comprehensive treatment plan. The conversation begins not with the question “What hurts?”, but with what the child likes to do and what the family’s daily life is like.
The same physical therapist before, during, and after surgery —the therapist present in the operating room—conducts rehabilitation starting on the first day of recovery. The child exercises with someone they already know, which reduces anxiety and facilitates a return to physical function. This is particularly important during limb lengthening, when systematic physical therapy is crucial for maintaining joint mobility.
Comprehensive care in one place —X-rays, blood tests, an orthotist, a psychologist, a dietitian, a speech therapist, and certificates for schools and government offices are available without unnecessary referrals or having to search for other facilities. Surgeries are performed at our partner hospital, Medicover, where the Paley European Institute team cares for the patient from admission through discharge.
Support for families from other cities and countries —families traveling here for medical treatment receive assistance with arranging transportation, accommodations, and all the logistics of their stay.
Parents' Council —parents who have themselves undergone treatment at the Paley European Institute—regularly test and evaluate new approaches, helping to shape the model of care.
Why does family involvement improve treatment outcomes?
Parents who understand the treatment plan are better able to follow rehabilitation recommendations at home and recognize signs that require contacting a doctor more quickly. Thanks to preparing the family for home care, children who undergo surgery at the Paley European Institute stay in the hospital for an average of only 2 days. A shorter hospital stay and less stress lead to a more peaceful recovery and a better quality of life for the entire family.

Related articles

Diagnosis and Treatment Methods for Childhood Cerebral Palsy (MPD).
What is SEMLS surgery, and who needs it?
Childhood Cerebral Palsy: What Every Parent Should Know

Childhood cerebral palsy - diagnosis and comprehensive care at Paley European Institute

When is cerebral palsy diagnosed?
Cerebral Palsy Treatment Methods.
MPD and hip problems - how do hip reconstructions support a child's development and mobility?
MPD and hip prevention in children

MPD is not a sentence – the story of a mother who trusted the process

Cerebral palsy (MPD).
The Most Famous People with MPD - Did You Know?

Causes and Risk Factors for the Development of Childhood Cerebral Palsy (MPD).

Rehabilitation of Children with Childhood Cerebral Palsy (MPD).

Types and Forms of Childhood Cerebral Palsy (MPD).

Specific Aspects of Cerebral Palsy
The use of botulinum toxin in neurology
Genetic defects

Serial plaster casting in pediatric therapy: How rehabilitation camps support development and treatment
Your Most Frequently Asked Questions About Neuromuscular Disorders
These are conditions in which damage to the nervous system or muscles disrupts muscle tone, strength, and coordination. They include, among others, MPD, spina bifida, SMA, Rett syndrome, and familial spastic paraparesis.
Most commonly, delayed motor development, increased or decreased muscle tone, walking on tiptoes, contractures, hip pain, scoliosis, and foot deformities.
Hypertonia is increased muscle tone (spasticity or stiffness), while hypotonia is decreased muscle tone, in which the muscles are flaccid. Both are symptoms, not separate diseases.
The disease cannot be reversed, but orthopedic surgeries correct its effects: contractures, hip instability, and limb deformities. They improve gait, reduce pain, and increase independence.
This is a multi-stage procedure in which several problems affecting the lower limb—such as the hip, knee, and foot—are corrected during a single anesthesia session. As a result, the child undergoes just one surgery and one rehabilitation process instead of several.
Not at the Paley European Institute. We operate on both hips in a single procedure without a cast, and rehabilitation begins the very next day.
When an X-ray shows a progressive subluxation or dislocation of the hip, or when the hip is painful and makes it difficult to sit or walk. Early detection through regular checkups allows for treatment to be planned before a dislocation occurs.
See our patients before treatment
See Our Patients During Treatment